
Double Board Certified · Functional Nasal Surgery
Turbinate Reduction — restoring airflow without sacrificing function.
Enlarged turbinates are a common, often overlooked cause of a nose that's always stuffy. Turbinate reduction shrinks them to open the airway while keeping the tissue that warms and humidifies the air you breathe. It's often done in the office or alongside septoplasty.
ABFPRS
Facial Plastic & Reconstructive Surgery
ABOto
Otolaryngology — Head & Neck Surgery
AAFPRS
Fellowship Director
In Consultation
"The turbinates are part of healthy nasal function. The goal is to reduce — never to remove."

A Note from Dr. Mourad
"Inferior turbinate hypertrophy is one of the most common — and most under-recognized — causes of chronic nasal obstruction. The right operation reduces the bulk of the turbinate while carefully preserving its critical role in conditioning the inspired air."
— Dr. Moustafa Mourad, MD
Medically reviewed by Moustafa Mourad, MD, FACS — dual board-certified in Facial Plastic & Reconstructive Surgery and Otolaryngology–Head & Neck Surgery; Clinical Assistant Professor of Otolaryngology at New York Medical College; AAFPRS Fellowship Director. The medical review identifies the anatomy, evidence, limits, and questions patients should understand before choosing a procedure.
Last reviewed: June 2026
Key takeaways
- Turbinate reduction shrinks enlarged inferior turbinates to widen the nasal airway.
- The turbinates' role in warming, humidifying, and filtering air is preserved, not removed.
- It is considered when hypertrophy causes obstruction that medical therapy hasn't relieved.
- Modern technique is conservative, preserving the mucosa to avoid empty-nose symptoms.
- It is frequently combined with septoplasty when both contribute to obstruction.
Overview
What is turbinate reduction?
Turbinate reduction is a procedure that shrinks enlarged inferior nasal turbinates — the long ridges of tissue and bone along the side walls inside the nose — to restore the cross-sectional area of the nasal airway. The goal is to relieve chronic nasal obstruction while preserving the turbinates' essential job of warming, humidifying, and filtering inspired air.
It is considered when turbinate hypertrophy has been documented on examination, is causing meaningful obstruction, and has not adequately responded to optimized medical therapy — typically intranasal steroids, antihistamines, and saline irrigation given a fair trial. Turbinate reduction is frequently combined with septoplasty when both contribute to obstruction.
Modern technique is conservative. Submucosal radiofrequency or coblation, or limited submucous resection, reduces the underlying volume while preserving the mucosa. Complete turbinectomy is avoided because it can cause empty-nose symptoms; the operation is designed to relieve obstruction without compromising nasal function.
Turbinate reduction can be performed in the office in appropriately selected patients, particularly when minimally invasive submucosal or radiofrequency techniques are appropriate. Local anesthesia is typically sufficient and the procedure is relatively brief. Congestion, crusting, or mild blood-tinged drainage can occur afterward, but downtime is typically limited and many patients can return to work within 1–2 days. Nasal airflow continues to improve as swelling resolves over the following several weeks.
Turbinate reduction at a glance
What it does: shrinks enlarged inferior turbinates to open the airway.
Techniques: radiofrequency, submucosal (microdebrider), or outfracture — chosen by what is enlarged: soft tissue, bone, or position.
Setting: in office under local anesthesia for radiofrequency; operating room when combined with septoplasty.
Recovery: congestion and crusting for 1–2 weeks; most patients return to work in a few days.
Breathing improves gradually over several weeks as swelling settles. The turbinate lining and its role in conditioning air are preserved.
An Established Academic Authority
Double board certification. Fellowship director. Published author. A surgeon's surgeon.
ABFPRS
Board Certified
American Board of Facial Plastic & Reconstructive Surgery
ABOto
Board Certified
American Board of Otolaryngology — Head & Neck Surgery
NYMC
Clinical Assistant Professor
Otolaryngology · Clinician Scholar Pathway
AAFPRS
Fellowship Director
American Academy of Facial Plastic and Reconstructive Surgery
Textbook
Published Author
Contributions to the academic literature of facial plastic surgery
Dual board certification in both Facial Plastic & Reconstructive Surgery and Otolaryngology — Head & Neck Surgery.
01 · Why Dr. Mourad
A surgeon trusted by surgeons for this operation.
Dr. Moustafa Mourad is double board-certified by the American Board of Facial Plastic & Reconstructive Surgery and the American Board of Otolaryngology — Head & Neck Surgery, and serves as an AAFPRS Fellowship Director.
The practice concentrates on the operations of the face, nose, and sinuses — and on the patients other surgeons have found challenging.
Every consultation is unhurried, every plan is individual, and no operation is recommended unless it is the right one.
02 · Ideal Candidates
Who benefits most from this operation.
Candidacy is determined together at consultation. The most satisfied patients share three things in common.
I
Chronic Congestion
Persistent bilateral nasal obstruction, often worse at night or when lying on one side, that does not respond fully to medical therapy.
II
Allergic Component
Patients with chronic allergic rhinitis whose turbinates remain enlarged despite topical steroids and allergy management.
III
Concurrent Septal Surgery
Frequently combined with septoplasty when both contribute to the obstruction — addressing only one rarely fully resolves the breathing problem.
Illustrated Anatomy
How turbinate reduction restores the airway.
Turbinate reduction acts on internal nasal anatomy that does not appear in external photographs. The illustration shows enlarged inferior turbinates encroaching on the nasal airway, which the procedure is designed to debulk while preserving the functional mucosal surface.
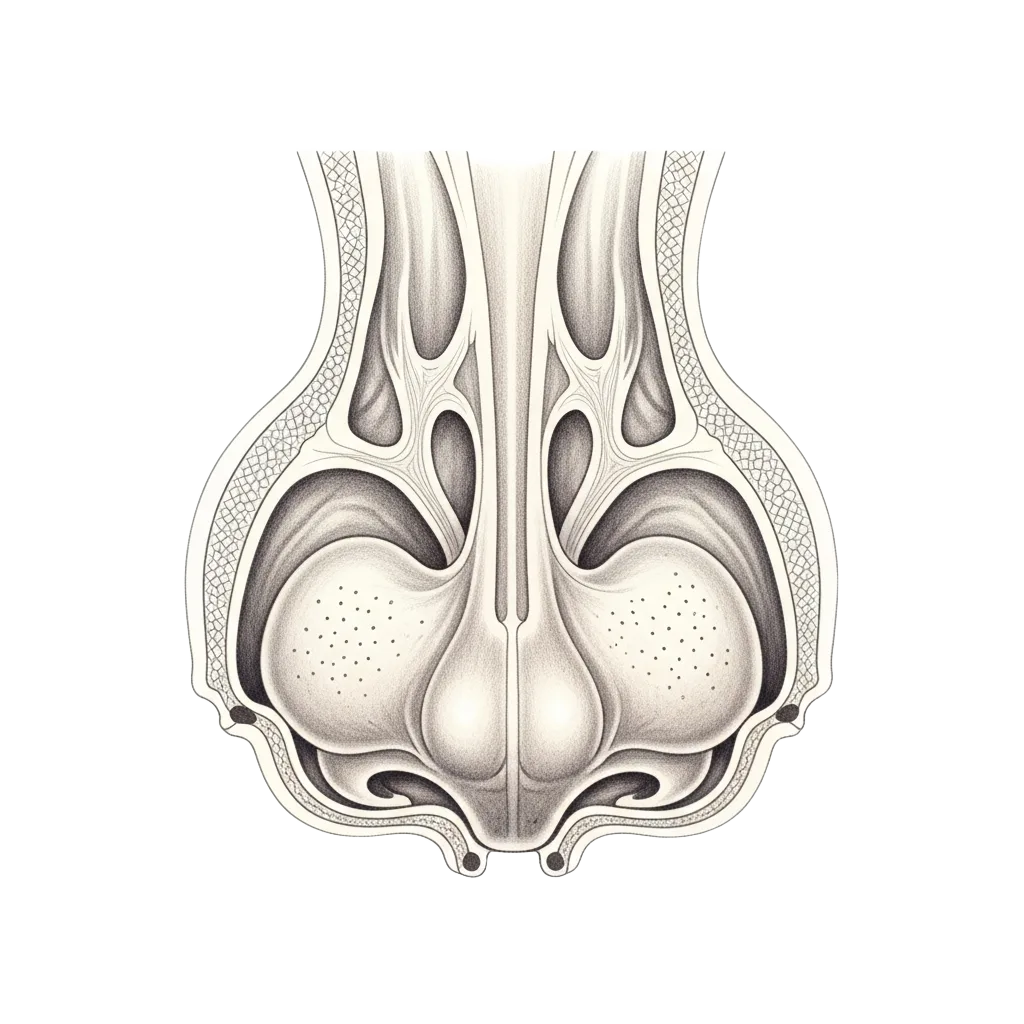
Illustrative anatomy · Not a patient photograph
If this describes you, the next step is a quiet, unhurried conversation — not a sales call.
An Honest Note
When this operation may not be right for you.
Patients whose obstruction is primarily septal should have a septoplasty first, with turbinate reduction reserved for residual symptoms.
Aggressive over-resection causes empty nose syndrome — a recognized complication that conservative technique is designed to avoid.
Patients with active rhinosinusitis are treated medically before any turbinate procedure.
Inadequately managed allergic disease should be optimized first; surgery is not a substitute for medical therapy.
03 · Approaches
The full range of options.
Turbinate reduction is not a single technique. The right method depends on the dominant contributor — bone, mucosa, or position — and on what other airway problems need to be addressed at the same setting.
1 of 6 · Submucosal Resection
04 · Technique
Submucosal vs radiofrequency reduction.
Modern turbinate reduction is conservative. The goal is meaningful airway widening with the mucosa preserved — never aggressive resection.
Submucosal
Microdebrider Reduction
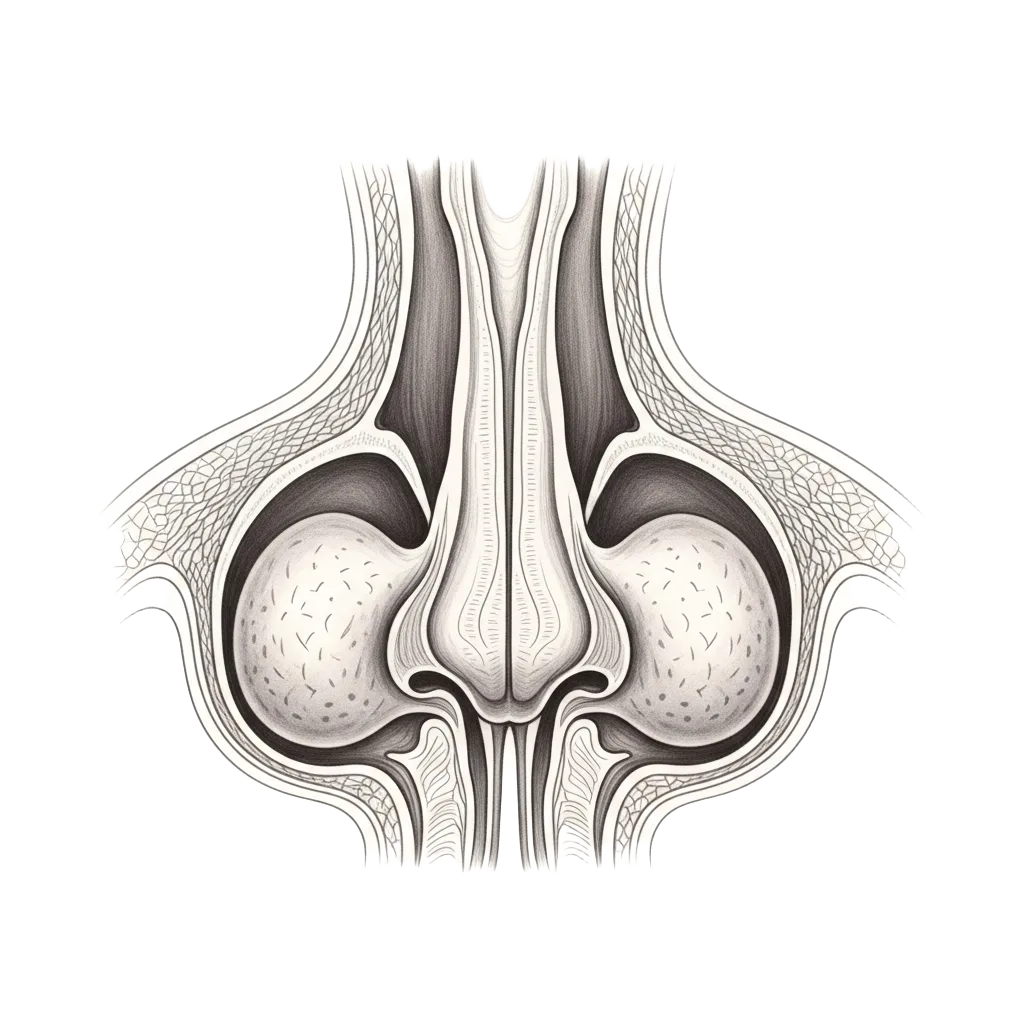
A small incision in the front of the turbinate provides access to the submucosal tissue. A microdebrider removes the bulk of the underlying tissue while the surface mucosa is preserved intact.
This is the workhorse procedure for significant turbinate hypertrophy and is highly effective when combined with septoplasty.
Radiofrequency
In-Office Option
A small radiofrequency probe is introduced into the turbinate to shrink the submucosal tissue. It can be performed under local anesthesia in the office for selected patients.
It is well-suited to milder, primarily mucosal hypertrophy and to patients who wish to avoid the operating room.
Illustrative diagrams. Conservative technique preserves the critical function of the turbinate.
Begin the conversation
Chronic congestion that medical therapy has not solved — there is often a structural answer.
Cost & Insurance
Turbinate Reduction Cost & Insurance in NYC
Turbinate reduction cost depends on the technique used, whether it is performed alone or combined with septoplasty or other nasal airway surgery, the type of anesthesia, and the surgical setting. Treatment is planned individually after a nasal airway evaluation.
MouradNYC is an out-of-network practice. Eligible medically necessary functional components may be submitted to insurance when the patient's plan includes applicable out-of-network benefits and plan requirements are met. Coverage, authorization, deductibles, coinsurance, allowed amounts, and patient responsibility vary by plan and are not guaranteed. Verification and authorization do not guarantee payment. Our office can help review benefits and assist with preauthorization when appropriate.
What May Affect Cost
- Reduction technique used
- Whether septoplasty is combined
- Type of anesthesia
- In-office vs operating room setting
- Prior nasal treatment
- Insurance plan requirements
The prices listed are provided as general estimates of typical surgical investment and are not guaranteed quotes. Surgical fees vary based on the patient's anatomy, the complexity of the procedure, previous surgery, operative time, anesthesia and facility requirements, implants or hardware, virtual surgical planning when applicable, and whether multiple procedures are performed together. An exact surgical fee is provided following consultation and development of an individualized treatment plan.
05 · In Dr. Mourad's Words
Educational videos.
Short educational films and patient perspectives from the Manhattan practice.
Dr. Mourad in Practice
An overview of the practice and philosophy.
Patient Perspective
A patient discusses her experience before, during, and after surgery.
Inside the Consultation
How Dr. Mourad evaluates anatomy, goals, and candidacy.
06 · Recovery
What healing actually looks like.
Stage 01
First 24 Hours
Mild congestion and crusting through the first few days are typical. No external dressings are required.
Stage 02
Week 1
Through the first week, saline irrigation supports healing. Most patients return to office work within a day or two.
Stage 03
Weeks 2 – 4
Through weeks two to four, congestion steadily clears and airflow improves. Final airway gain is often appreciated by one month.
Stage 04
Months 1 – 12
Long-term, the conservative reduction is stable, the mucosal function is preserved, and the improvement is durable.
Have a specific question?
Send a brief note describing your anatomy or concerns — the office will route it directly to Dr. Mourad for review.

Before You Arrive
Your consultation, prepared.
Bring records of any allergy testing or medical therapy you have tried.
Note all topical nasal sprays you currently use — including any over-the-counter decongestants.
Bring prior CT imaging if available.
List current medications and supplements.
Allow 45 minutes for a focused nasal examination, often including endoscopy.
Be prepared to discuss whether septoplasty should be planned at the same time.
Patient Perspectives
From patients of the practice.
I had used decongestant sprays daily for almost a decade. After turbinate reduction I weaned off them completely, which I did not think was possible.
Dr. Mourad explained why aggressive turbinate removal could create a different problem and recommended a conservative submucosal approach. That kind of restraint is rare.
The procedure itself was quick and the recovery was modest. What changed was the simple act of breathing through my nose during exercise.
Individual experiences. Results and recovery vary by patient. Testimonials shared with written consent.
Patient Reviews
Turbinate Reduction Patient Experiences
Selected public patient reviews. Individual experiences vary.
“I can now say I can breathe better than I ever have”
Real patient experiences
Selected public reviews from patients of the practice.
Your privacy matters
We never share personal health information.
Board-certified expertise
Dual board-certified facial plastic and reconstructive surgeon.
Individual results vary. Reviews reflect individual experiences and are not a guarantee of outcome.
At a Glance
Turbinate reduction fact snapshot.
- What it does
- Shrinks enlarged inferior turbinates to open the airway.
- Techniques
- Radiofrequency, submucosal microdebrider, or outfracture — chosen by what is enlarged: soft tissue, bone, or position.
- Setting
- In office under local anesthesia for radiofrequency; operating room when combined with septoplasty.
- Recovery
- Congestion and crusting for 1–2 weeks; most return to work in a few days.
- Breathing improves
- Gradually over several weeks as swelling settles.
- Preserves
- The turbinate's lining and its role in conditioning air.
Frequently Asked
Patient questions, honestly answered.
Determining the dominant problem starts with history and a focused exam. We perform topical decongestion in clinic and assess change under endoscopic view; mucosal swelling often shrinks, while bony prominence persists. Palpation and endoscopy guide whether imaging is necessary, and CT is reserved for unclear or revision cases. Identifying mucosal versus bony causes is essential because it directs whether energy‑based shrinkage or tissue/bone removal is required.
The goal is to preserve mucosal surface and function while relieving obstruction. When surgeons remove excessive mucosa or over-resect tissue, dryness and crusting can follow; a preservation‑first approach reduces that risk. Most modern techniques target submucosa or underlying bone while leaving mucosal cover intact. Risks are discussed in detail during consultation, and postoperative care focuses on humidification and saline irrigation to support mucosal recovery.
Clinical references
This page draws on published clinical practice guidelines and public-health references. These sources inform general patient education and do not replace an individual evaluation with Dr. Mourad.
- 01American Academy of Otolaryngology–Head and Neck Surgery Foundation. Clinical Consensus Statement: Septoplasty with or without Inferior Turbinate Reduction. Otolaryngology–Head and Neck Surgery. 2015;153(5):708–720. AAO-HNSF consensus
- 02U.S. National Library of Medicine (MedlinePlus). Nose Injuries and Disorders. MedlinePlus
The Most Important Step
Your expert consultation.
A turbinate evaluation is a careful functional examination — confirming that turbinate hypertrophy is contributing to the obstruction, ruling out other causes, and recommending the conservative procedure that fits.